TSH and Free T4 Results Explained: Reading a Korean Thyroid Report (2023 Range 0.6–6.8)
Updated 4 November 2026 · General health information, not medical advice. Your doctor interprets your own results.
Quick answer: TSH (thyroid-stimulating hormone) is the brain’s signal to the thyroid, and free T4 is the active thyroid hormone in your blood. They move in opposite directions: a high TSH usually points to an underactive thyroid, a low TSH usually points to an overactive one, and free T4 tells you how far things have gone. If TSH is high but free T4 is normal, that is called subclinical hypothyroidism. Korea’s thyroid society now uses a Korean TSH reference range of 0.6–6.8 mIU/L (instead of the older 0.4–4.0), so a TSH of 4.0–6.8 is no longer treated as a disease by that guideline. Always compare against the range printed by your own lab.

Why TSH and free T4 are read together
Your pituitary gland, at the base of the brain, makes TSH to tell the thyroid how much hormone to produce. When the thyroid is underperforming, the pituitary “shouts louder” and TSH rises. When the thyroid makes too much hormone, the pituitary goes quiet and TSH falls. That is why, according to MedlinePlus (US National Library of Medicine), a high TSH level usually means hypothyroidism and a low TSH level usually means hyperthyroidism.
T4 (thyroxine) is the main hormone the thyroid releases. Most of it is bound to proteins in the blood; the small unbound part is free T4, the form your body can actually use. MedlinePlus notes that experts consider free T4 testing more accurate than total T4 and is usually ordered together with TSH. Both MedlinePlus and the US National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK) describe the same logic: TSH is the first screen, and free T4 (sometimes with T3 and thyroid antibodies) shows what kind of problem it is.
One limit matters: a TSH test cannot tell you the cause of a thyroid problem. That takes other tests, such as antibody tests.
The four basic patterns
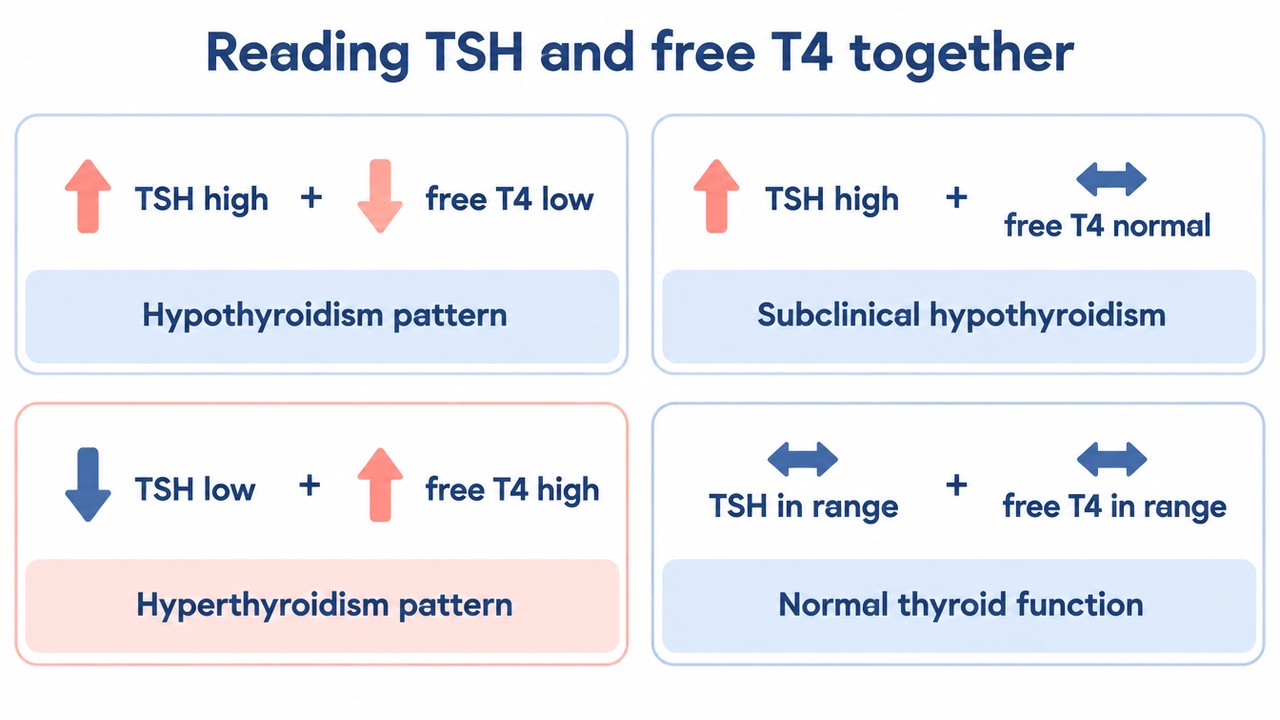
| TSH | Free T4 | Usual name | What it often means |
|---|---|---|---|
| High | Low | Hypothyroidism pattern | The thyroid is not making enough hormone |
| High | Normal | Subclinical hypothyroidism | Early or mild underactivity; often watched first |
| Low | High | Hyperthyroidism pattern | The thyroid is making too much hormone |
| In range | In range | Normal thyroid function | No thyroid hormone problem shown |
The Korea Disease Control and Prevention Agency (KDCA) health portal describes hypothyroidism in the same terms: low free T4 with high TSH, while subclinical hypothyroidism is normal free T4 with a mildly raised TSH. In Korea, the KDCA notes that Hashimoto’s thyroiditis, an autoimmune condition, causes about 70–85% of primary hypothyroidism. On the overactive side, the KDCA says Graves’ disease accounts for about 60–80% of hyperthyroidism, with an incidence of about 0.72 per 1,000 people a year, most common between ages 50 and 54, and people in their 30s to 50s making up about two-thirds of patients.
Korea’s 2023 TSH range: why your report may look “high” when it isn’t
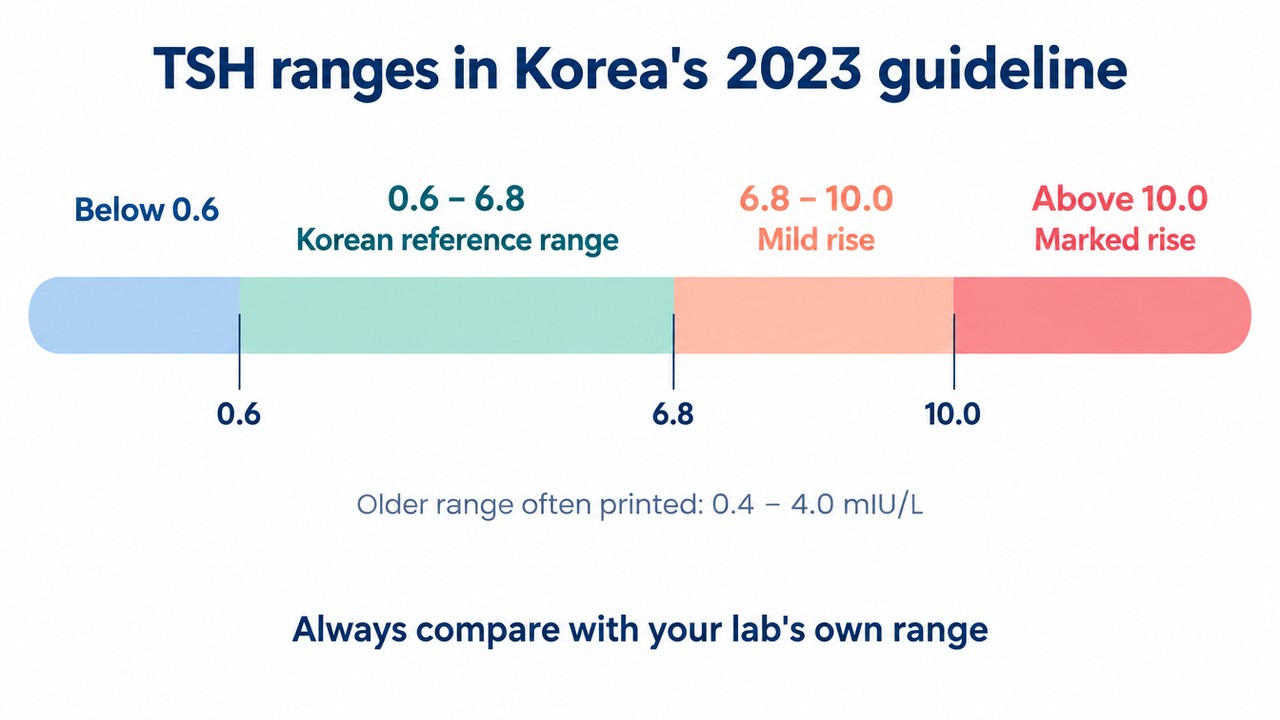
Many lab reports still print a TSH reference range of roughly 0.4–4.0 mIU/L. That range came largely from US and European studies. In 2023 the Korean Thyroid Association (KTA) published a guideline on subclinical hypothyroidism, summarised in the Korean Journal of Medicine, which set a Korean TSH reference range of 0.6–6.8 mIU/L, based on Korea National Health and Nutrition Examination Survey data.
| KTA 2023 term | TSH (mIU/L) | Free T4 |
|---|---|---|
| Korean reference range | 0.6–6.8 | In range |
| Mild subclinical hypothyroidism | 6.8–10.0 | In range |
| Severe subclinical hypothyroidism | Above 10.0 | In range |
| Older range still printed by many labs | 0.4–4.0 | — |
Three practical consequences follow from the guideline:
- TSH between 4.0 and 6.8 is no longer subclinical hypothyroidism under the KTA definition, even if your report flags it “H”.
- About 90% of subclinical hypothyroidism is the mild type (6.8–10.0).
- The number depends on the test kit. The guideline gives kit-specific equivalents of the 6.8 cut-off: about 5.2 mIU/L on an Abbott assay, 6.9 on Siemens and 7.4 on a Beckman RIA kit. So the same blood could read differently in two hospitals. That is why the range printed by your lab, and your doctor’s reading of it, matter more than any single number online.
Pregnancy is different: the guideline uses an upper TSH limit of 4.0 mIU/L in the first trimester, and MedlinePlus also notes pregnancy changes thyroid results. MedlinePlus adds that TSH can run higher in people over 80 and can drop temporarily during serious illness.
Worked examples: four results, read step by step
These are invented examples to show the logic, not diagnoses.
| Example | TSH (mIU/L) | Free T4 | How the KTA 2023 framework reads it | Typical next step to discuss |
|---|---|---|---|---|
| A. Age 45, routine test | 5.2 (report range 0.4–4.0, flagged H) | In range | Inside the Korean 0.6–6.8 range, but check which kit your lab uses: on a kit where 6.8 ≈ 5.2, this sits at the upper edge | Ask whether your lab’s range is the Korean one; often just recheck later |
| B. Age 52, tired | 7.5 | In range | Mild subclinical hypothyroidism (6.8–10.0) | Repeat TSH and free T4 in 2–3 months without medication; TPO antibody test |
| C. Age 60 | 12.0 | In range | Severe subclinical hypothyroidism (above 10.0) | Treatment may be considered, especially with heart disease or high cholesterol |
| D. Age 38, palpitations | 0.05 | High | Hyperthyroidism pattern | Further tests for the cause (for example antibodies) |
Example B is the most common situation. The KTA recommends re-measuring after 2–3 months, because a single raised TSH often settles, and suggests a TPO (thyroid peroxidase) antibody test to see whether autoimmune thyroiditis is behind it. The KDCA notes that subclinical hypothyroidism progresses to overt hypothyroidism in about 5% of people a year, and suggests rechecks every 6–12 months for those being watched.
Who gets treated, and who usually doesn’t
The KTA 2023 guideline is fairly conservative:
- Age 70 and over: treatment of subclinical hypothyroidism is not recommended.
- Adults under 70: consider levothyroxine only for severe subclinical hypothyroidism (TSH above 10) when there is heart disease, heart failure or dyslipidaemia.
- Treating mild subclinical hypothyroidism just to relieve vague symptoms is not recommended.
The KDCA’s own patient page lists situations where treatment is commonly considered, such as TSH above 10, positive antibodies, planning a pregnancy or high cholesterol, and notes that after starting thyroid hormone the dose is usually checked again after 6–8 weeks. If you are planning a pregnancy or are pregnant, tell your doctor about any TSH result, because the pregnancy threshold is lower.

Things that can skew your numbers
- Medicines: MedlinePlus says birth control pills, steroids and some other medicines can affect T4 results, and that you may need to stop certain medicines before a TSH test. Tell your doctor everything you take, but don’t stop any medicine unless your doctor tells you to.
- Iodine: the KDCA points out that Korean diets already provide about 20 times the iodine the body needs, and that taking kelp or seaweed supplements can cause temporary hypothyroidism. More iodine is not a fix.
- Recent illness: serious illness can lower TSH for a while (MedlinePlus).
- Different hospitals, different kits: compare results from the same lab where possible.
If you are also reading other numbers on the same report, see our guides to liver enzymes AST and ALT, cholesterol, LDL, HDL and triglycerides (high cholesterol is one reason doctors look harder at a raised TSH), and fasting glucose and HbA1c.

Checklist before your follow-up visit
| Bring or ask | Why |
|---|---|
| Your report with the lab’s printed TSH and free T4 ranges | Ranges differ between kits and hospitals |
| A list of medicines and supplements (including kelp/iodine) | They can change results |
| Earlier thyroid results, if any | Trends matter more than one value |
| “Should I repeat this in 2–3 months?” | The KTA recommends a repeat test for a raised TSH |
| “Is a TPO antibody test useful for me?” | It helps show whether autoimmune thyroiditis is likely |
| Pregnancy plans | The first-trimester TSH limit is lower (4.0) |
Frequently asked questions
Q. My TSH is 5.0 and the report says “H”. Do I have hypothyroidism?
Not necessarily. Under the Korean Thyroid Association’s 2023 guideline, the Korean TSH reference range is 0.6–6.8 mIU/L, so a TSH between 4.0 and 6.8 is no longer classed as subclinical hypothyroidism. Your lab may still print the older 0.4–4.0 range, and the exact cut-off depends on the test kit, so ask your doctor how your lab’s number should be read.
Q. What does high TSH with normal free T4 mean?
That combination is called subclinical hypothyroidism. Under the KTA 2023 guideline, TSH of 6.8–10.0 is mild and above 10.0 is severe; most cases are mild. The usual first step is a repeat TSH and free T4 test after 2–3 months, often with a TPO antibody test.
Q. Is free T4 better than total T4?
MedlinePlus says medical experts consider the free T4 test more accurate than total T4, so it is used more often. Total T4 measures free and protein-bound hormone together. Either way, a T4 result alone can’t diagnose a thyroid problem, so it is usually done with a TSH test.
Q. Should I take seaweed or iodine supplements if my thyroid is slow?
No, not without your doctor’s advice. The KDCA notes that Koreans already get about 20 times the iodine they need from food, and kelp supplements can actually cause temporary hypothyroidism.
Q. I’m over 70 with a mildly high TSH. Will I need medicine?
Often not. The KTA 2023 guideline does not recommend treating subclinical hypothyroidism in people aged 70 and over, and TSH naturally tends to run higher in older people (MedlinePlus notes this especially over 80). Your doctor will still look at symptoms, free T4 and other conditions.
Sources
- MedlinePlus (US National Library of Medicine), TSH (thyroid-stimulating hormone) test (checked 4 November 2026)
- MedlinePlus, Thyroxine (T4) test (checked 4 November 2026)
- NIDDK, Thyroid tests (checked 4 November 2026)
- Korea Disease Control and Prevention Agency, National Health Information Portal, Hypothyroidism (checked 4 November 2026)
- Korea Disease Control and Prevention Agency, National Health Information Portal, Hyperthyroidism (checked 4 November 2026)
- Korean Thyroid Association, Diagnosis and Management of Subclinical Hypothyroidism: The 2023 Clinical Practice Guideline, Korean Journal of Medicine (checked 4 November 2026)
This article is general health information, not medical advice. It was written with AI assistance and fact-checked against official sources. Only your doctor can interpret your results and decide on treatment.




One Comment